ID
Image Findings
Cystic Lung disease
More ID Fun?
Random?!
Final Jeopardy
100
What is the first line treatment and duration, PaO2 <60
Bactrim and steroids for 21d: PJP
Presentation: sub-acute illness of fever, dry cough, fatigue, fever
Dx: BAL w/ microscopy, PCR; others markers include LDH and BDG
Tx: 21 days of TMP-SMX (alternatives include dapsone + TMP, primaquine + clindamycin, atovaquone, IV pentamidine)
If PaO2 <60, or A-a gradient ≥ 35mmHg add corticosteroids within 3 days of Tx.
Prednisone 40mg BID for 5 days, then 40mg daily for 5 days then 20mg prednisone until day 21.
100
What is this finding?
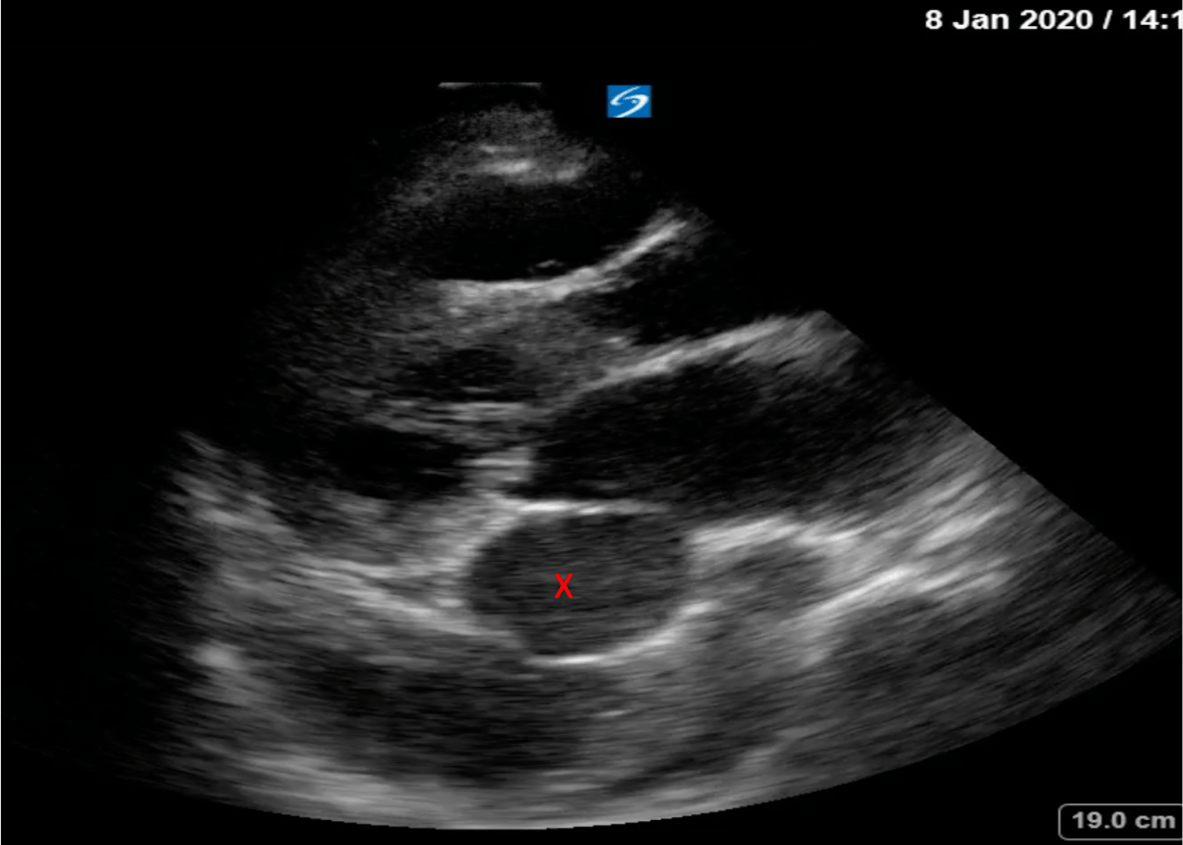
Coronary sinus
100
What VEGF-D level is significant for LAM
>800
100
What Legionella serotype is the most common?
Serotype 1; urine antigen testing targeted for serotype 1 which accounts for 80% of cases.
A negative urinary antigen test does not exclude Legionella pneumonia.
Lower respiratory tract specimen for Legionella PCR and/or culture on buffered charcoal yeast extract (BCYE) agar.
100
What is Diagnosis?
Silicosis
Risk associated with particle exposure. In US significant risk is coal mining.
Imaging: nodular, upper lobe, hilar lymph nodes with “eggshell calcifications”
Can present as alveolar proteinosis (PAP) acutely
Increase risk for lung cancer.
Increase risk for TB infection.
200
What disease state is this?
Blastomycosis
Diagnosis: Antigen detection: urine, serum, BAL, 1,3 β-d-glucan
Gold standard: culture “broad-based budding"
Tx:
Mild – Moderate: itraconazole for 6 – 12 months
Severe amphotericin B for 1-2 weeks then itraconazole
200
pt is a 45yo smoker.. What disease state is most likely?

PLCH
200
What two criteria can you use to diagnose a chylothorax

Pleural triglycerides >110 or positive chylomicrons in pleural fluid
200
diagnosis?

Coccidiomycosis:
Commonly diagnosed as CAP in endemic regions (southwestern US, Mexico). However, may have more pronounced eosinophilia, hilar lymphadenopathy and erythema nodosum.
Dx: antigen or antibody testing. Histopath w/ isolation of spherules.
Tx:
Immunocompetent: observation
Immunocompromised (or severe disease): fluconazole
200
What is the only cause of low pH <7.4 and transudative pleural effusion?
Urinothorax
Pleural Creatinine: Serum creatinine >1
A technetium 99m renal scan can be considered confirmatory test
A technetium-99m-labeled renal tracer is injected intravenously.
Renal filtration/excretion: The tracer is taken up or filtered by the kidneys and excreted into the collecting system and urinary tract.
Urinary leakage: If there is a disruption of the urinary tract (such as ureteral obstruction with forniceal rupture, trauma, or instrumentation), radiotracer-containing urine leaks into the retroperitoneum.
Urine can migrate through diaphragmatic defects or lymphatic pathways into the pleural cavity.
300
These two fungal infections do not express Beta d glucan, what are they?
Crypto and Mucor
early blasto also has negative big
300
Adult Patients present with fever, cough, weight loss, malaise, and shortness of breath.What disease state is this classic for?
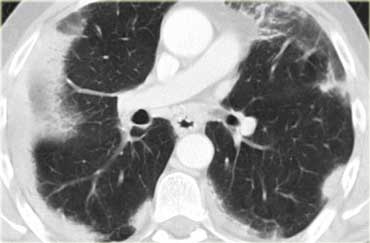
Chronic eosinophilic pneumonia is an idiopathic condition characterized by filling of the alveoli with eosinophils.
It is associated with an increased number of eosinophils in the peripheral blood.
The symptoms are often severe and last three months or more. Patients respond promptly to treatment with steroids
300
This signaling pathway is constitutively activated in LAM due to mutations affecting TSC1 or TSC2.
What is the mTOR pathway?
300
Based on the 2019 ATS/IDSA CAP guidelines when should follow-up chest imaging be obtained?
Answer: No follow up imaging
Recommendation. In adults with CAP whose symptoms have resolved within 5 to 7 days, we suggest not routinely obtaining follow up chest imaging (conditional recommendation, low quality of evidence).”
300
A patient with longstanding rheumatoid pleuritis develops a milky pleural effusion. Pleural fluid analysis reveals cholesterol of 350 mg/dL, low triglycerides, and no chylomicrons.
What is the diagnosis?
Answer: What is pseudochylothorax?
Teaching pearl: Chylothorax is a lymphatic disorder; pseudochylothorax is a chronic cholesterol-rich pleural effusion.
Pleural fluid cholesterol >200 mg/dL (often substantially elevated).
Triglycerides typically < 110 mg/dL
Chylothorax: Leakage or obstruction of the thoracic duct or its tributaries results in accumulation of triglyceride-rich lymphatic fluid
Pseudochylothorax: Chronic pleural inflammation, cellular degeneration, and impaired cholesterol clearance result in cholesterol accumulation.
400
Based on the 2020 ATS/ERS/ESCMID/IDSA Guidelines name 2 of the 3 microbiologic criteria for NTM Dx?

400
What is this image representative of?

Radiographic findings in pulmonary alveolar microlithiasis. a) Chest radiograph depicting a fine, sand-like micronodular pattern with basilar predominance. b, c) High-resolution computed tomography with posterior lower lobe and anterior upper lobe micronodules, interlobular septal thickening, subpleural emphysema with predominance of small cysts. d) Mediastinal windows reveal calcific burden in the parenchyma and most concentrated in a peripheral septopleural location.
400
A patient with LAM has progressive decline in FEV1 and worsening chylous pleural effusions. What targeted therapy addresses the underlying pathophysiology?
What is sirolimus?
400
Pt. presented to the ED w/ son, requiring emergent intubation. Pt. is an exterminator and Tx a previously condemned home approx. 7 days ago. Patient unfortunately passed in 24hrs. Cultures remain negative. What is the most likely cause?
Answer: Hantavirus Cardiopulmonary syndrome (HCPS)
S/S: fever, myalgia
Vector: rodents (deer mice) urine, feces, salvia
Imaging: bilateral pulmonary infiltrates/airspace disease
Dx: CDC ELISA for IgM testing, can see thrombocytopenia, increase LDH
Tx: Broad spectrum Abx, ECMO
Case fatality rate of 36%.
400
A patient is Dx with TB and HIV (CD4 < 50). At what point should ART begin?
Answer: < 2 weeks of TB Tx
CD4 < 50 initiate ART within two weeks of TB Tx
CD4 > 50 initiate ART within 2 – 8 weeks of TB Tx
TB meningitis: do not start ART until after at least 2 weeks of TB Tx and meningitis resolved.
Immune reconstitution inflammatory syndrome (IRIS):
Unmasking IRIS: new presentation of subclinical infection
Paradoxical IRIS: deterioration of Tx infection
Addition or prednisone can reduce risk of IRIS
500
Based on the 2020 ATS/ERS/ESCMID/IDSA Guidelines what is the difference in MAC Tx of nodular/bronchiectatic vs cavitary (assuming you are treating)?
Answer: three times weekly vs. daily
Pt.’s w/ MAC should have susceptibility-based Tx for macrolides and amikacin.
M. kansasii susceptibility Tx for rifampicin.
M. abscessus should have erm(41) gene sequencing (for macrolide resistance).
Noncavitary MAC (nodular/bronchiectatic) Tx: 3 drug regimen (including macrolide and ethambutol) three times a week.
Cavitary 3 drug regimen (including macrolide and ethambutol) daily.
If failed Tx after at least 6 mths then add amikacin liposome inhalation suspension (ALIS).
Neither inhaled amikacin or ALIS should be used in newly Dx.
Treatment for at least 12months after culture conversion (ie, negative culture)
500
Daily Double
What is this?

500
A patient has diffuse cystic lung disease, normal VEGF-D, no angiomyolipomas, and no evidence of tuberous sclerosis. Does a normal VEGF-D exclude LAM? What is next step?
A normal VEGF-D does not exclude LAM; lung biopsy may be needed if diagnostic certainty is required.
500
Patient reports worsening shortness of breath and lymphadenopathy. Patient works w/ removal of small game, rodents and rabbits. What is the Tx?
Tx: Aminoglycoside (streptomycin, gentamicin)
Francisella tularenis (Tularemia)
Vector: tick bites, small game and rodents, carcass/hides, rabbit
Gram negative coccobacillus
Presentation:
Ulceroglandular ulceration of the skin
Glandular lymphadenopathy
Tx: aminoglycoside, cipro
500
TB Dx: Rank in order from highest yield to lowest yield for TB:
A. Prebronch sputum
B. Transbronchial biopsy
C. Bronchial Wash
D. Post-bronchoscopy sputum
Answer: A > D > B > C
TB Diagnosis:
Acid-fast bacilli (AFB) smear. 3 specimens Results in hours
Poor sensitivity and specificity but increases w/ each sample
Liquid and solid mycobacterial Cx’s. Results in 2-8 weeks
Volume should be at least 3mL, but optimal is 5-10mL.
Nucleic acid amplification test (NAAT): Mycobacteria Tuberculosis Direct (MTD), Bronchoscopy:
Pre-bronch sputum collection: 67%
Post-bronch sputum collection: 35%
Transbronchial biopsy: 20%
Bronchial wash: 4%
500
A patient with a large solitary fibrous tumor of the pleura presents with recurrent episodes of severe fasting hypoglycemia. Insulin and C-peptide levels are suppressed. What paraneoplastic syndrome explains this presentation?
What is Doege-Potter syndrome?
A paraneoplastic syndrome characterized by hypoglycemia associated with a solitary fibrous tumor of the pleura (SFTP).
Pathophysiology:
Tumor produces excessive amounts of incompletely processed IGF-2 (high-molecular-weight IGF-2 or “big IGF-2”).
IGF-2 has insulin-like activity.
Results in non-islet-cell tumor hypoglycemia.
C-peptide is released in equimolar amounts with endogenous insulin when proinsulin is cleaved. Since pancreatic beta cells are appropriately suppressing insulin secretion, C-peptide is also low.