Ant. Compartment of Upper Arm
Vasculature
Brachial Plexus
Clinical Applications
QoD
100
Name this muscle.
What is the short head of the biceps brachii?
100
 Identify #16.
What is the subclavian a.?
100
Name the two main branches that emerge from the posterior cord.
What are axillary n. and radial n.?
100
28 y/o male presents to the ED with moderate shoulder and upper arm pain. Name the nerve roots that innervate the deltoids and the anterior upper arm muscles.
What are C5 and C6 (axillary and musculocutaneous nerves)?
100
A lesion in the upper brachial plexus roots gives rise to this neurological condition which presents as weakness in abduction/flexion of the shoulder joint, pronated forearm, and paresthesia/numbness on the lateral aspect of the arm and forearm.
What is Erb-Duchenne's palsy?
200
Name the movements facilitated by the coracobrachialis mm.
What are adduction and flexion of the shoulder joint?
200
Name the point at which the axillary artery turns into the brachial artery.
What is the inferior border of the teres major?
200
Name the two nerves that branch off of the superior trunk.
What are the suprascapular n. and the nerve to subclavius?
200
40 y/o male presents to the clinic for his annual well visit. Subjective history reveals that the patient has been experiencing a tingling sensation in his right forearm and digits, so you decide to perform a DTR on the elbow. 4+ reflex noted on the right extremity compared to 2+ on the left. State which type of neurological legion this is.
What is an upper motor neuron lesion?
200
A patient falls backwards and tries to break their fall with their upper limb hyperextended. Name the type of fracture they might experience as a result of this.
What is a supracondylar humeral fracture?
300
This is the origin of the coracobrachialis.
What is the coracoid process of the scapula?
300
Name the two branches of the middle portion of the axillary artery.
What are the thoracoacromial a. and lateral thoracic a. ?
300
A lesion in the lateral cord of the brachial plexus would lead to these nerves being affected. State whether the deficits would be sensory, motor, or both.
What are musculocutaneous n. (both), lateral cord of median n. (both), and lateral pectoral n. (motor)?
300
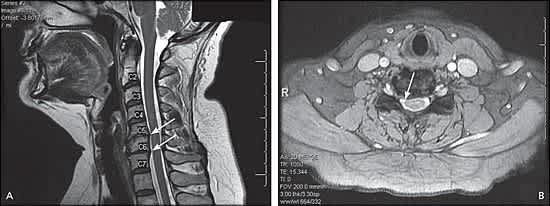 Name 3 functional deficits (motor and sensory) you would expect to see based on these images.
What are:
1. weakness in abduction of shoulder
2. weakness in elbow supination when elbow is flexed
3. paresthesia or numbness in lateral aspect of forearm
*Pictured is C5-C6 radiculopathy where the nerve roots are being impinged. Compression of these nerve roots would lead primarily to deficits in muscles and cutaneous regions innervated by the axillary n., musculocutaneous n.
300
A fracture of the surgical neck of the humerus would endanger these arteries and this nerve.
What are the posterior and anterior circumflex humeral a. and the axillary n.?
400
This is the insertion of the brachialis mm.
What is the ulnar tuberosity and coranoid process of ulna?
400
This is the inferior-most branching of the brachial a. (*Hint: a collateral artery)
What is the inferior ulnar collateral a. (which anastomoses with the posterior ulnar recurrent a.)?
400
Identify #17.
What is the posterior cord?
400
75 y/o male presents to the office with complaints of left-sided pectoral weakness. Upon exam, you notice weakness in adduction, medial rotation, and flexion of the shoulder joint. Additionally, there appears to be instability in the scapula. Name the two muscles that are affected, their innervations, and nerve roots.
What are the pectoralis major (innervated by lateral and medial pectoral n.) and pectoralis minor (innervated by medial pectoral n.)?
lateral pectoral n. (C5-C7)
medial pectoral n. (C8-T1)
400
This symptom is characteristic of both Volkmann's ischemic contracture and Klumpke's palsy. Explain the difference between the two.
What is "claw hand"?
In compartment syndrome, the arterial supply to the forearm becomes blocked due to excess fluid compressing the brachial a., therefore the flexor muscles of the wrist become infarcted and permanently contracted.
In Klumpke's palsy, there is a laceration in the lower brachial plexus which supplies C8 and T1 nerve roots to the median, radial, and ulnar nerves which innervate the forearm muscles. Damage to these nerves results in impaired motor function of these muscles as well as paresthesia in coordinating cutaneous nerves.
500
This is the extension of the biceps brachii tendon that blends into the deep fascia of the forearm as well as providing a roof for the cubital fossa.
What is the bicipital aponeurosis?
500
The subscapular a., which branches from the axillary a., gives rise to these two arterial branches.
What are the thoracodorsal a. and circumflex scapular a.?
500
Identify #20
What is the long thoracic n.?
500
56 y/o male presents to the ED with an acute MI and tragically passes away. Autopsy reveals that there was significant calcified plaque build up in his vessels leading to athersclerosis of his brachial arteries. Name the lateral branches of the brachial artery and their anastomoses that allowed this patient temporary bypass of the sclerotic artery.
What are the
-radial collateral a. which anastomoses with the radial recurrent a.
-medial collateral a. which anastomoses with the interosseus recurrent a.?
500
The symptoms of this syndrome closely mimic those of Klumpke's palsy due to the C8 and T1 nerve roots innervating the same regions.
What is Horner's syndrome?