STOP-BANG!
Wide Awake
Leg day, every night
Wildcard
100
Patients can underestimate the importance of healthy sleep. List 4 potential consequences of untreated OSA
Neurobehavioural: daytime sleepiness, depressed mood, decreased quality of life, memory, task concentration, and work performance, increased work absenteeism and risk of motor vehicle accidents.
Cardiovascular: hypertension, CAD, atrial fibrillation, cerebrovascular disease, heart failure.
100
Identify at least 3 factors that are associated with an increased risk of developing insomnia
Predisposing: age, female, chronic pain, depression/anxiety/mood disorders
Precipitating: stressful life events, medical disorders/surgeries (OSA), shift work, travel, medications AE
Perpetuating: cognitive, behavioural, psychological beliefs
100
What patient population(s) has a higher prevalence of RLS?
Pregnant women in third trimester, age > 50, neurodegenerative conditions
100
Besides CPAP, what other options are available for the management of OSA?
Lifestyle changes, pharmacotherapy for weight loss, positional therapy, mandibular advancement splint, upper airway surgery (UPPP), hypoglossal nerve stimulation
200
What screening questionnaires are required before a GP can order a Medicare-rebated sleep study?
Epworth Sleepiness Scale score of ≥8, plus a positive result on one risk-stratification tool — STOP-Bang ≥4, OSA-50 ≥5, or a high-risk Berlin Questionnaire
200
What two sleep disorders often co-incide with each other, and what is this condition called?
COMISA
OSA and Insomnia - 30-50% of OSA patients also have insomnia
200
Name 3 secondary causes of Restless leg syndrome?
- Iron deficiency with or without anemia
- End-stage kidney failure
- Peripheral neuropathy
- Inflammatory conditions: celiac disease, rheumatoid arthritis, inflammatory bowel disease 45
- Psychiatric: depression, anxiety disorders
- Neurological: Parkinson's, MS, polyneuropathies, spinal cord diseases
- Drugs: SSRIs, metoprolol, lithium, H1 antihistamines, dopamine antagonists, mirtazapine
200
Which of these historical figures does NOT have a documented struggle with a sleep disorder?
A) Vincent van Gogh
B) Marilyn Monroe
C) William Howard Taft
D) Albert Einstein
Albert Einstein. He's actually the opposite case — famously a long sleeper, reportedly getting 10+ hours a night
Vincent van Gogh struggled with severe insomnia and tinnitis
Marilyn Monroe had chronic insomnia, reportedly linked to industry pressure, and her dependence on sleeping pills and barbiturates contributed to her death.
William Howard Taft (27th US President) is a commonly cited historical case of obstructive sleep apnoea, based on his obesity and well-documented episodes of falling asleep during meetings and public events.
300
Besides the classic obese, middle-aged male with a thick neck who drinks & smokes, name another patient group you should still suspect for OSA — and what clinical features should you look for on examination?
Post-menopausal women, Down's Syndrome
Normal BMI with craniofacial abnormalities (Mallampati >3, retrognathia/micrognathia, high arched or narrow hard palette, macroglossia, enlarged tonsils)
300
A patient wants to know what medication options exist for insomnia. What would you tell them, and what's the general principle guiding how these are used?
Melatonin, BZEs, BZE agonists 'Z' drugs, Orexin antagonists, Anti-histamines, Mirtazapine, Quetiapine
Short term, lowest dose for shortest duration < 4 weeks for acute insomnia
Emphasise importance of good sleep hygiene and CBT-i
300
Patients describe the RLS sensation in all sorts of ways. What key descriptors in the history would support the diagnosis?
uncontrollable urge to move legs & uncomfortable sensation in legs, coca-cola in the veins, crawling, burning, itching, achine, symptoms worse at night and with immobility, relief with movement/walking
300
A 6-year-old wakes screaming and inconsolable about 90 minutes after falling asleep, with no memory the next day. What is this phenomenon, and which sleep stage does it arise from?
Night terrors (sleep terrors) - arise from slow-wave (deep NREM) sleep, usually in the first third of the night. Distinguish from nightmares, which occur in REM and are remembered.
400
A 54-year old commerical truck driver with known OSA on CPAP, BMI 34, comes in for a fitness to drive assessment. Can you sign him off? What will you tell him?
No you cannot. For a commercial licence, Austroads requires confirmed treatment compliance and a satisfactory response to treatment, certified through an annual sleep specialist review, not GP sign-off alone.
Compliance is objective — CPAP data showing ≥4 hours/night on ≥70% of nights — and "satisfactory response" means resolved daytime sleepiness (repeat Epsworth).
Your job as GP is ordering/following up the sleep study, having the driving-risk conversation, and referring him on for that specialist review.
400
A 45-year old man comes to you and says he's "just not sleeping well" for the last 7 months. What key questions would differentiate primary insomnia from OSA, RLS, a circadian rhythm disorder, or depression?
Clarify pattern - trouble falling asleep, staying asleep, or waking early
Clarify sleep DURATION and TIMING
- bedtime, fall asleep, wake up time, time they get out of bed
(early waking → depression; frequent waking → OSA, RLS, pain; can't fall asleep → anxiety, RLS, delayed sleep phase).
The key discriminator: does he actually doze off involuntarily during the day, or just feel tired? True dozing points to OSA or another hypersomnolence disorder
400
A 58-year old lady has chronic persistent RLS that is significantly affecting her quality of life. What are the pharmacological options and potential side effects you'd counsel her on?
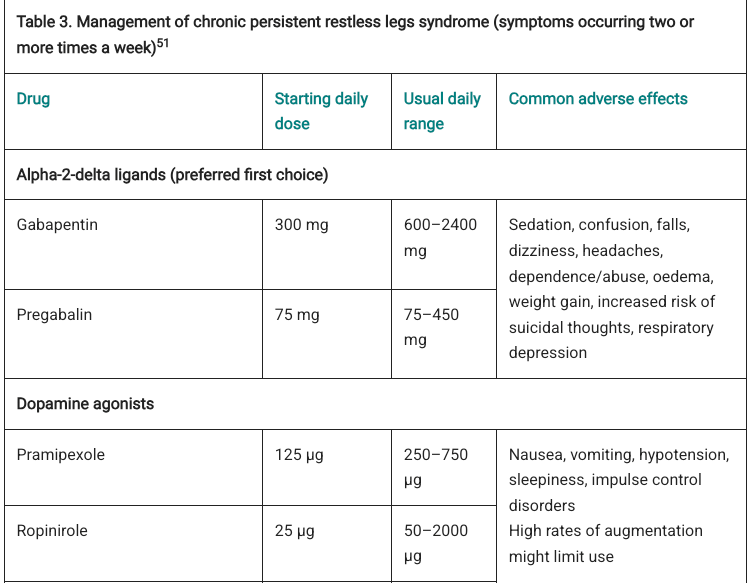
Infrequent symptoms (<2x/week) — low-dose levodopa (with benserazide or carbidopa), before bed or as needed
Frequent symptoms (>2x/week) — a gabapentin or pregabalin, preferred
400
A 65-year old man acts out his dreams — punching and kicking during sleep, and remembers vivid dreams matching the movements. Name the parasomnia and one important long-term association to screen for.
REM sleep behaviour disorder. Important association: 60-70% will have a neurodegenerative disorder (e.g. Parkinson's disease, Lewy body dementia) in 10 years