bph: alpha blockers vs 5-alpha-reductase inhibitors
androgen deprivation therapy 1
androgen deprivation therapy 2
treating erectile dysfunction
potpourri
200
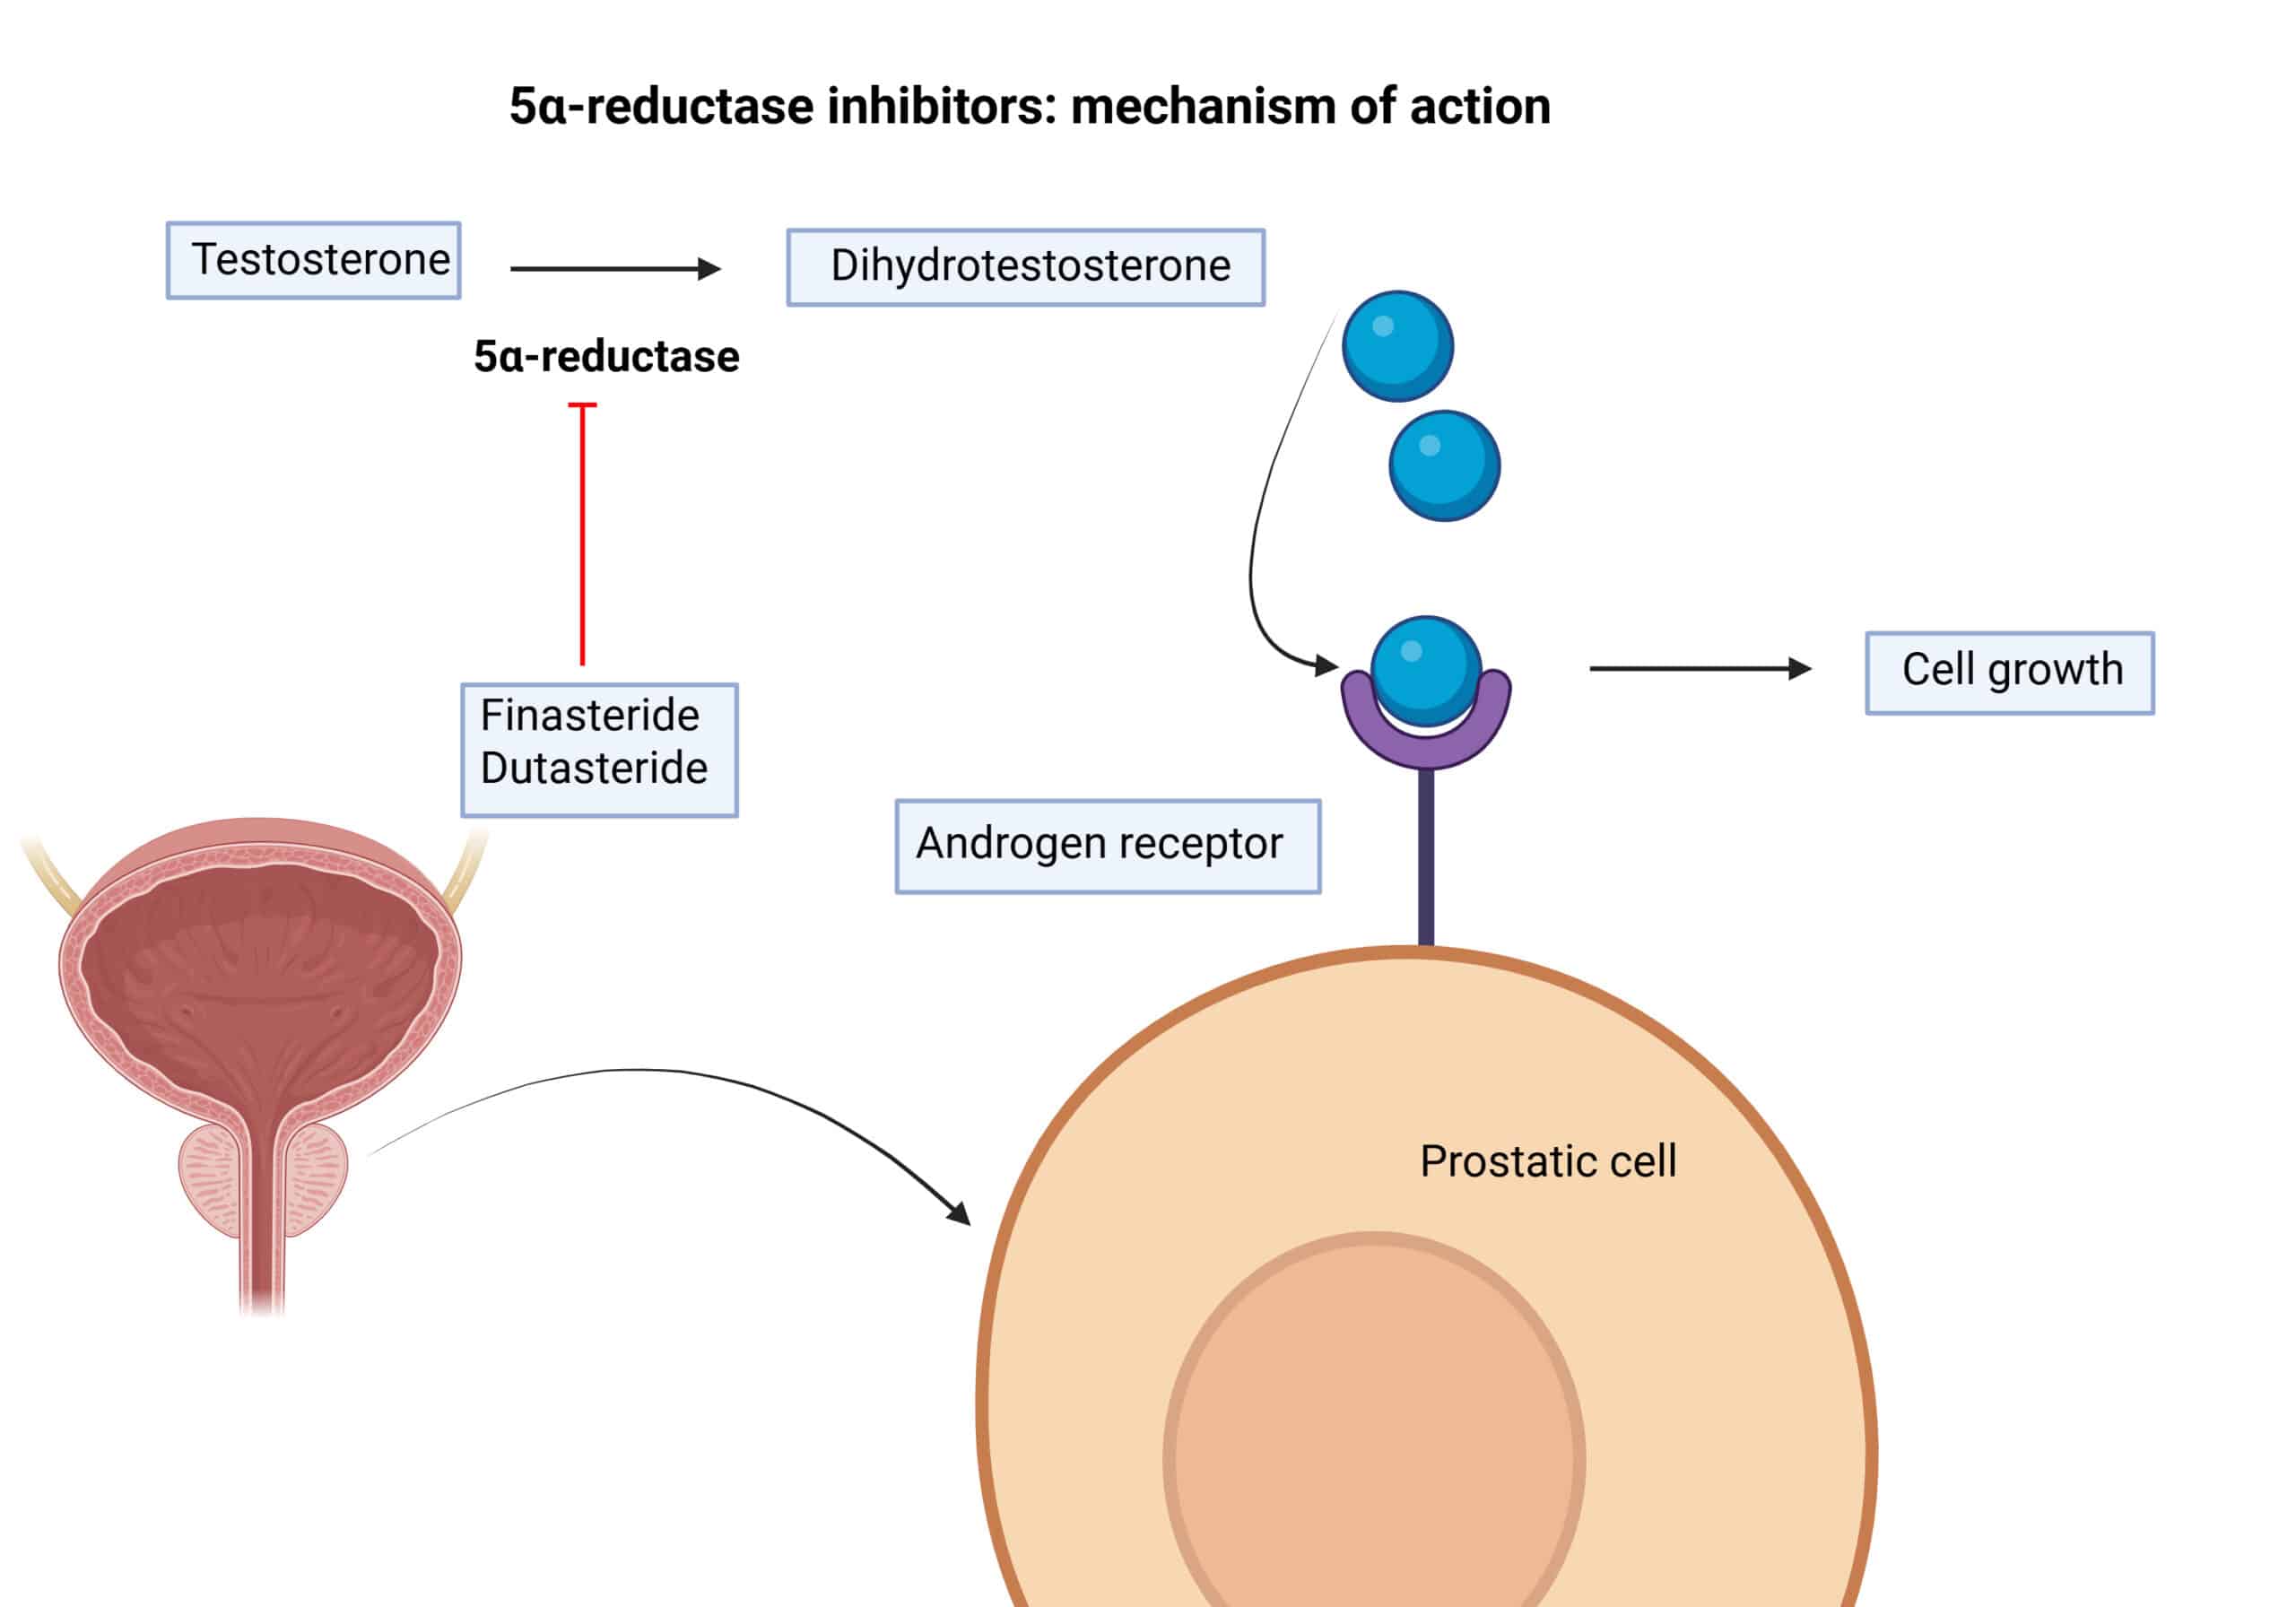
Finasteride shrinks the prostate by blocking this reaction
what is testosterone to DHT
200
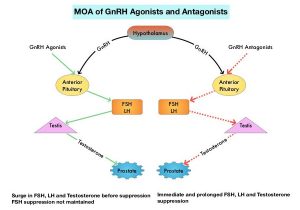
Leuprolide initially stimulates the pituitary GnRH receptor, as it belongs to this drug class
what are GnRH AGONISTs
200
The rationale for why drug classes are often combined/used in tandem in androgen deprivation therapy
Combined androgen deprivation therapy...
What is because it eliminates both testicular and secondary adrenal or tumor-produced androgens !!! Need comprehensive inhibition of multiple sites of testosterone synthesis in order to suppress growth.
200
This is a prerequisite for Seldenafil (or other PDE5 inhibitors) to be effective
What is sexual arousal
increased cGMP is downstream of sexual arousal
200
Your patient with BPH takes alpha blockers and 5-alpha-reductase inhibitors, and they are seeking medication to help with their erectile dysfunction. If you prescribe them the first line treatment, you should consider discontinuing this prior medication.
What are their 𝛼-Blockers! Combining two vasodilatory agents can cause profound hypotension
300
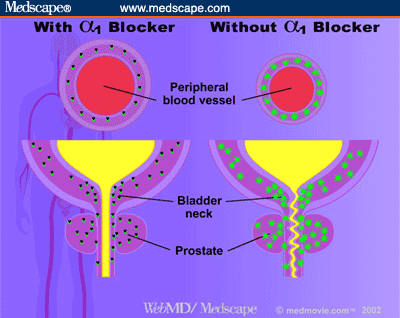
α1A-blockers reduce urinary outflow resistance at these TWO anatomic sites
what are 1. Bladder neck 2. prostatic urethra
300
Name two of the four class-wide ADT adverse effects
what are...
Class-Wide ADT Risks “BOCA”

Body composition changes: normally, testosterone ↑ protein synthesis/muscle and ↓ lipogenesis, so ↓ testosterone = "sarcopenic obesity”
Osteoporosis/fractures: normally, androgens → aromatase → estrogen → osteoclast inhibition, so ↓ androgens = more bone breakdown
CVD/metabolic risk: severe hypogonadism → "atherogenic" lipid shift → ↑ LDL and ↓ insulin sensitivity
Anemia: Normally, testosterone → kidneys → EPO, so ↓ testosterone = normocytic, normochromic anemia
300
1. This ADT may adversely cause hypokalemia, hypertension, edema, fatigue, and GI sx?
2. This drug should be co-prescribed with the above ADT to prevent these symptoms?
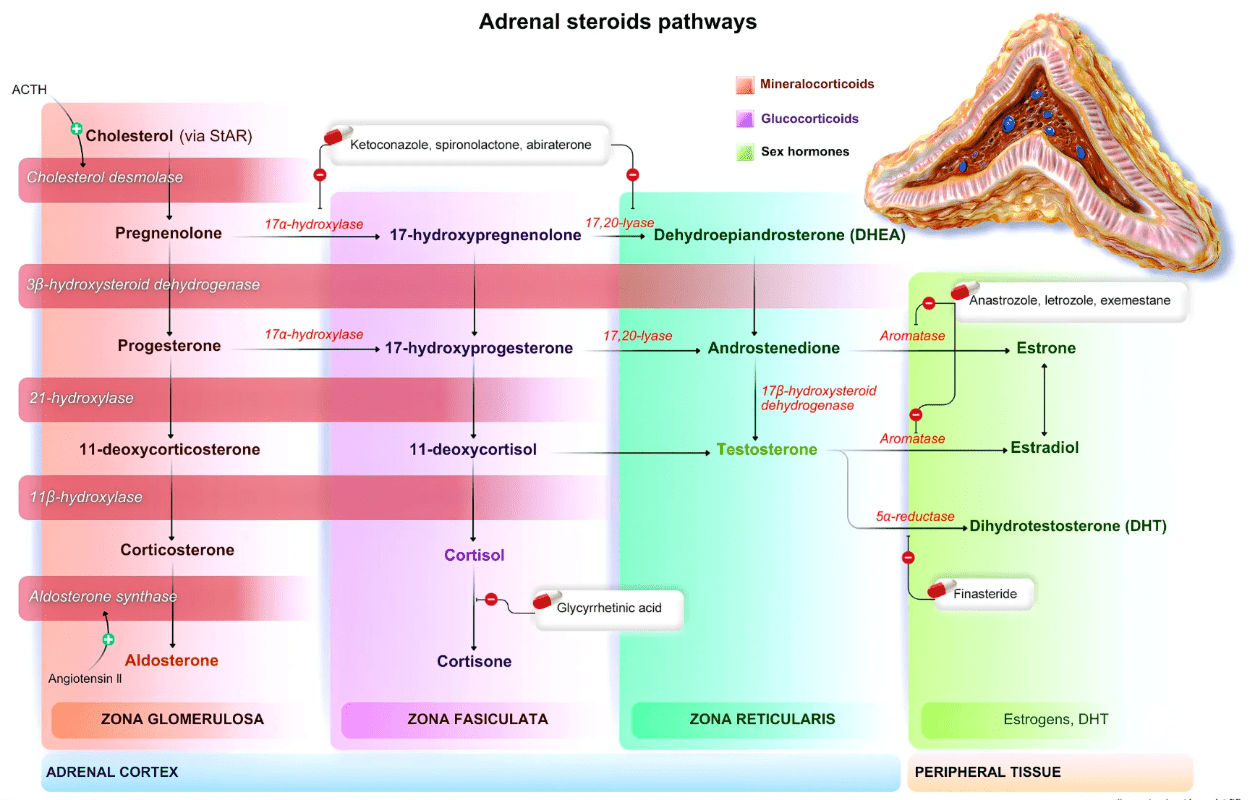
1. What is Abiraterone (CYP17 Androgen-Synthesis ⊢) inhibits 17α-hydroxylase, and 17,20-lyase, thus both TESTOSTERONE (and CORTISOL!) are not made.
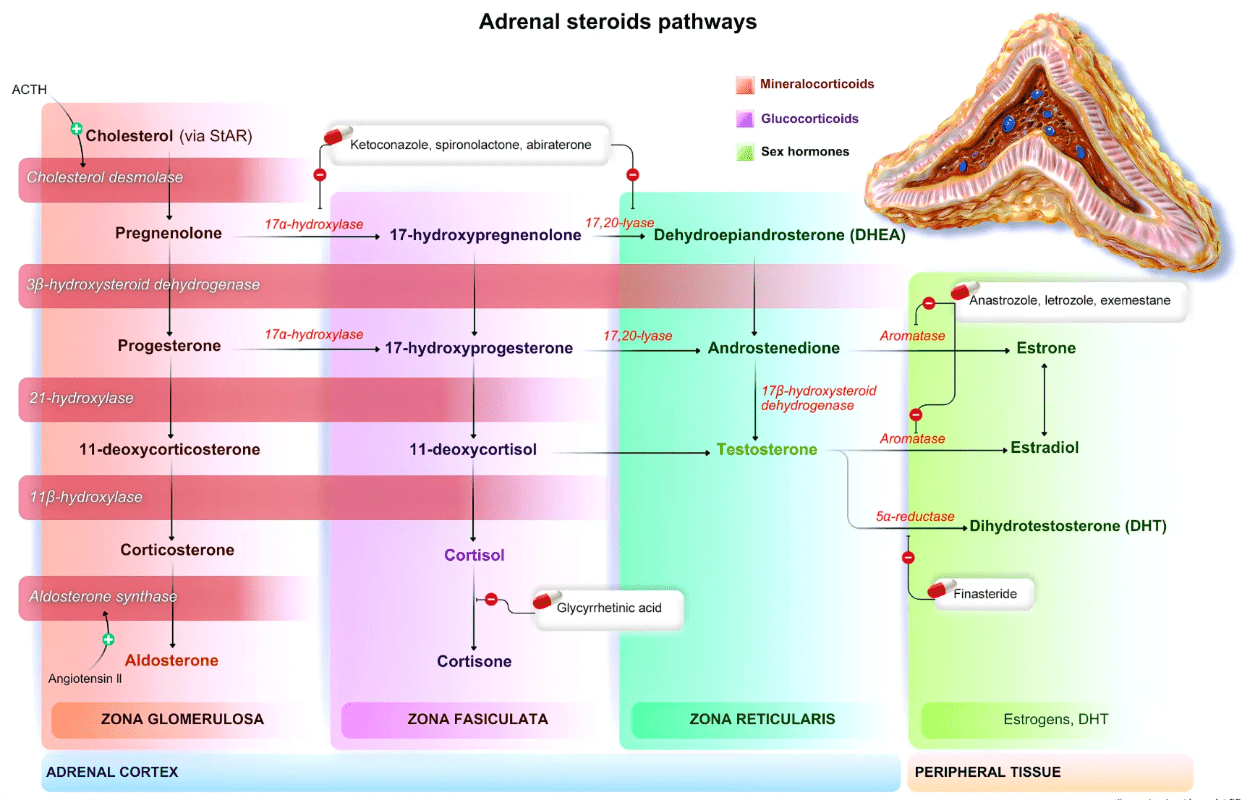
No cortisol --> no negative feedback to ACTH --> ACTH goes crazy --> promotes excessive mineralcorticoid synthesis --> HTN, hypoK, edema, etc.
2. What are glucocorticoids! BUT monitor for osteoporosis / bone wasting (a class-wide AE effect of ADT exacerbated by glucocorticoids)
300
Name any general vasodilatory adverse effects of Phosphodiesterase 5 (PDE5) inhibitors (Sildenafil, Tadalafil)
what are...

1. Headache (vasodilation, ↑ ICP, trigger for cluster headaches/migraines, etc.)
2. Flushing (vasodilation)
3. Dyspepsia (PDE5 ⊢ can relax the lower esophageal sphincter → reflux)
4. Nasal congestion (erectile tissue in there!)
5. Dizziness/ hypotension (dt relaxed vascular SM)
300
This PSA change is expected after approximately six months of finasteride therapy.
What is a 50% decrease?
400
This BPH therapy may cause retrograde flow as an adverse effect
what are 𝛼-Blockers (Tamsulosin (Flomax), Alfuzosin, Doxazosin)

400
Enzalutamide and apalutamide prevent testosterone from acting at this site
What are cancer cells in the prostate
Androgen-R Antagonists (2nd Gen): Displaces androgens from receptors on prostate cancer cells → blocks receptor signaling → reduces growth
400
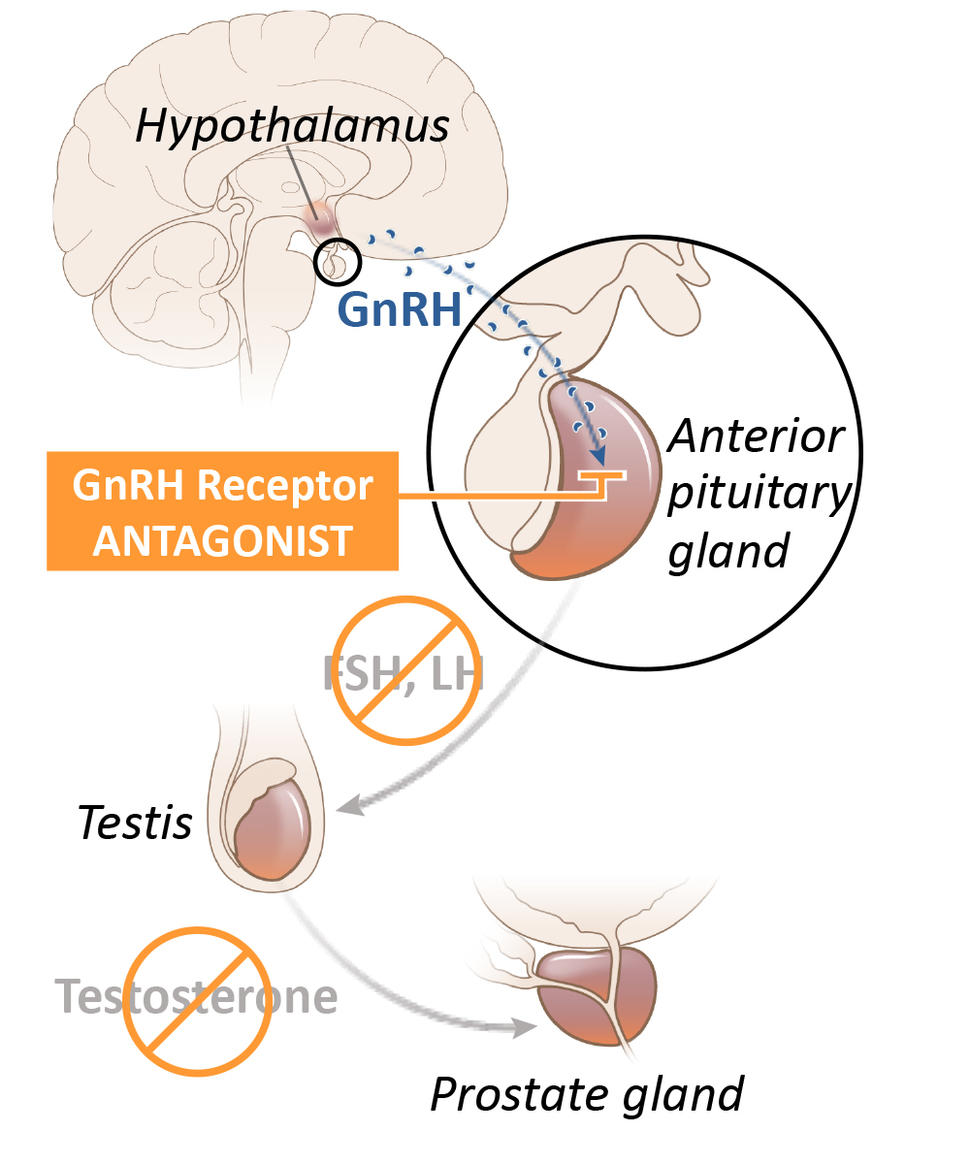
Degarelix and Relugolix (oral) act on the same site as Leprolide (GnRH Agonist) but have no risk of testosterone flare; they belong to this drug class.
what are GnRH Antagonists! Directly inhibit GnRH signaling to FSH/LH → ↓ testicular androgen production

"garlic breath is an instant turnoff" "degarelix?"
400
Sildenafil can also inhibit retinal PDE6, causing this characteristic adverse effect
What is vision loss
400
This med cass is absolutely contraindicated with PDE-5 inhibitors
What are organic nitrates

500
My patient has a large prostate and needs reduced long-term BPH progression. This medication should be prescribed
what are
Finasteride ± Dutasteride (5-𝛼 Reductase Inhibitors)

500
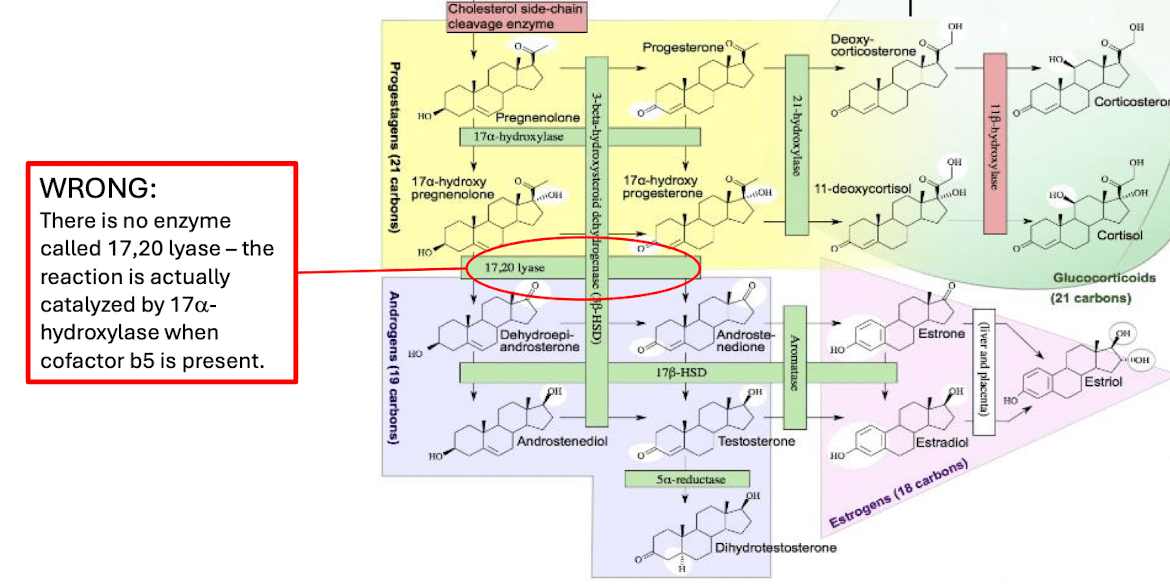
Abiraterone is a CYP17 Androgen-Synthesis inhibitor that acts at these two enzymes in the testosterone synthesis pathway
what are
1. 17α-hydroxylase ⊢
2. 17,20-lyase ⊢ (which according to JeffMD is actually 17α-hydroxylase + Cytochrome B5)
500
1st-generation androgen-R antagonists (bicalutamide, flutamide) are less effective than second-gens, but this is a specific instance they are used in
what is with GnRH Agonists (Leprolide, Goserelin) can initially cause a testosterone flare before receptor desensitization begins. This is prevented with a short course (~4 wks) of a first-gen anti-androgen (bicalutamide, flutamide) started prior to GnRH Agonists.
Why 1st gens? Many reasons, but one is that they are less potent than 2nd gens and therefore have less adverse effects
500
Sildenafil and tadalafil prolong the effects of cGMP by inhibiting this enzyme
what is Phosphodiesterase type 5 (PDE5)
Normal phys:
sexual stimulation → parasympathetic-mediated release of nitric oxide (NO) in the corpus cavernosum → NO activates guanylyl cyclase → ↑ cGMP → smooth
PDE5 normally degrades cGMP
Inhibit PDE5 → preserve cGMP → ↑ penile blood flow to facilitate* erection
500
Sexual dysfunction, ↓ libido, ED, ejaculatory dysfunction, gynecomastia are adverse effects belonging to this class of BPH meds