Digoxin Intro
Digoxin Presentation
Digoxin Treatment
Clonidine intro
Clonidine treatment
100
Name a natural source of cardiac glycosides
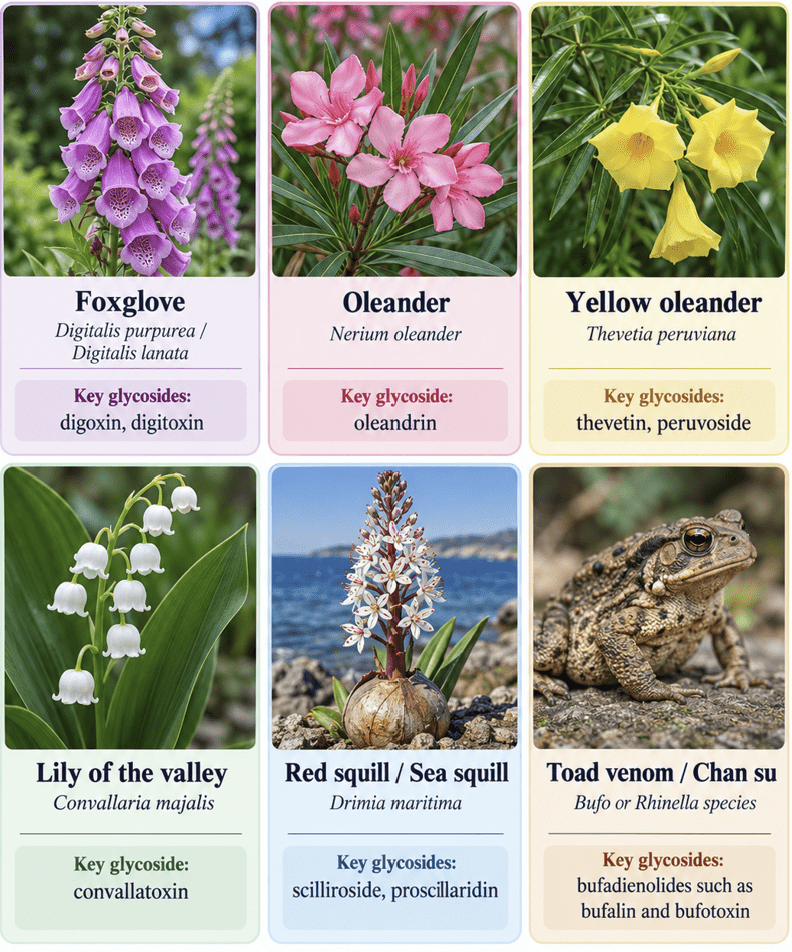
100
What are some possible ECG findings in digoxin toxicity (name 3)
- "Digitalis effect" - QT shortened (from shortened refractory period), scooping ST segment
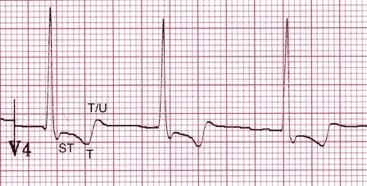
- Bradycardia, ventricular dysrhythmias (PVCs, VT, TdP, VF, Vflutter)
- Basically any except SVT (given AV nodal depressive effect)
100
Name treatment of digoxin that does not involve digoxin antibody fragments (Name 4)?
- Activated charcoal
- Fluid boluses
- Atropine
- Vassopressors/inotropes
- Lidocaine/Mg for wide complex arrythmia/TdP
- Not HD
100
What is the mechanism of action of clonidine?
Central pre-synaptic α2 receptor agonist → enhances activity of inhibitory neurons in vasoregulatory regions → decreased NE release
Imidazoline receptor agonist → decreased sympathetic outflow into periphery → reduces vascular tone/BP
?Some endogenous opioid effect
100
What sort of decontamination is indicated for clonidine/guanfacine overdose?
- AC 1g/kg if no contraindications
- May consider WBI for transdermal patches (massive drug reservoirs, 7.5mg clonidine with 70% remaining)
200
What is the mechanism of action of digoxin?
- Inhibition of Na/K-ATPase = increased Na intracellular = dysfunction of Na-Ca ion exchanger = More Ca intracellular = more for the SR
- Decreased AV conduction through increased vagal activity
200
What investigations would you order and when?
- All the usual stuff
- ECG
- K, Cr
- digoxin level 6 hours post ingestion/pre level/at time of unstable patient
200
After giving digoxin antibody fragment, how do you monitor the patient?
- Induces rapid reversible dysrhythmia (within 30 min)
- Monitor K Q1-2h post fab, rapid hypokalemia can occur
- Do NOT measure digoxin levels serially (commercial total digoxin assays measure both free digoxin and Fab-bound digoxin)
200
What is the presentation of clonidine overdose?
- Hemodynamics are biphasic, but within 1-2 hours bradycardia and ultimately hypotension (usually withing 4-8 hours)
- CNS depression (often fluctuating in pediatrics)
- Miosis
- Hypothermia and mild bradypnea (typically with significantly altered LOC)
200
A patient presents with hypotension, bradycardia, altered LOC and mild bradypnea. Will a stat urine tox screen aid in your treatment of the patient, why or why not?
No, does not detect clonidine/guanfacine and turn around time still likely >6h
300
Mechanism of Toxicity
- More ectopy/PVCs (increased Ca, closer to firing threshold DADs->PVCs)
- Increased automaticity/arrhythmias (shortened repolarization time)
- AV dissociation (directly blocks SA node)
300
Name 3 differences in the presentation of acute of chronic digoxin overdose
Acute: Younger, intentional ingestion, rapid onset GI symptoms, less neurologic symptoms, significant hyperkalemia, very high digoxin levels, more bradycardia
Chronic: Older, due to AKI/drug interactions(PGP), insidious GI effects, prominent weakness/confusion/delirium/blurred vision, N/low K, mildly elevated digoxin level, more ventricular dysarhythmias
300
How much digoxin antibody fragment should you give?
- Empiric = 10 vials IV push
- Serum level based or ingested mg based
- Chronic, likely just give 1 vial (can worsen Afib/CHF)
300
Why is clonidine prescribed in pediatrics (2 indications)
- Behavioral dysregulation
- Opioid sparing analgesia
- Sedation weans
- ADHD
- Tics
300
How do you dose high dose naloxone
- 2mg initially with rapid up titration for a 10mg dose (
400
Please explain the stone heart controversy
- Historically concern with IV Ca to patient with digoxin toxicity and hyperkalemia from 5 case reports in 1950s
- Lead to hypercontractility - "stone heart" and to cardiac arrest
- More beneficial to administer digiFab (reactivates the Na/K pump)
400
Name at least one of: A PK difference, a investigation difference or a treatment different for digitoxin vs digoxin toxicity
- PK: half life significantly longer (up to 7.5 days)
- Diagnosis: Commercial digoxin assays cross-react unpredictably with non-digoxin plant glycosides.
- Treatment: MDAC, may require larger doses
400
What are the indications for giving digoxin antibody fragment
- Unstable dysarrhythmias
- Severe hyperkalemia (?>5/5.5) - higher mortality
- Potential: digoxin level > 10, ingestion >10mg in adult
- Symptomatic chronic (dysrhythmias, significant GI symptoms, LOC changes)
400
How would a patient present 1 hour post a massive clonidine ingestion, why?
- Transient hypertension - Therapeutically, has little effect on peripheral α2 receptors, but are stimulated in overdose to cause temporary vasoconstriction and HTN
- Shortly afterward (1-2h) potent centrally mediated sympathetic inhibition becomes predominant effect
- Do not treat the hypertension!
400
How does guanfacine overdose change the presentation and treatment
- ER formulation, often delayed bradycardia and hypotension (12-18h) that lasts on average 36 hours
- Naloxone may be ineffective, rarely utilized
- Monitor for 24 h with ingestions
500
How do you treat clonidine overdose
- AC
- Fluids
- Atropine (bradycardia + hypotension)
- ?High dose naloxone - low responsive rate vs dose failures (then infusion 2/3 effective dose). If considering intubation, give 10mg
- Vasopressors