Open Drains
Closed Drains
Nursing, who?
What drain is that?
What would you do?
100
Define 'open drain'.
A surgically* placed tube/passage allowing passive* drainage of fluid into an absorbent dressing*, where the drain's contents are open to the atmosphere*.
50pts if not all points are covered.
100
Define 'closed drain'.
A drain that actively draws fluid100 from a wound via suction or vacuum100 system.
100
State THE most important nursing consideration for drain management.
Hand Hygiene100 and/or Aseptic Technique100
100
1)What drain is this?
2) Name 1 defining characteristic.

1) Yates drain 100
Any of the following:
2) Corrugated100 , open drain100 , passive drainage100 , soft tube100 , surgically placed100 .
100
Choose the most appropriate answer to the scenario below:
When changing the dressing over a Yates drain, you notice the drain has fallen out, along with the suture holding it in place. Do you:
a) Try to put it back in. There are no orders for its removal, and there is probably still fluid to drain from the wound.
b) Leave it out, clean the wound, redress the wound, and document in your progress notes.
c) Leave it out, clean the wound, redress the wound, document, and alert your shift c/o and treating team.
The most correct answer is c.
You would never try to push foreign matter back into the body, as it is now contaminated.
You should leave it out, clean the wound, redress the wound, and document.
However, you should notify the team and your shift c/o that it has been removed/fallen out so the patient's treatment plan can be adapted appropriately.
200
Name two types of open drains.
Penrose drain100
Yates drain100
200
State 2 benefits of using a closed drain.
Any two of the following:
Prevents fluid from accumulating in deep surgical spaces100
Facilitates quantifiable measurement of fluid100
Reduces risk of infection100 and haematoma100
Actively draws fluid100
200
Name 2 potential complications of drains, excluding infection.
Pressure injury (from tubing/device or from limited patient mobility).100
Delayed wound healing.100
Pain.100
Lengthened hospital stay.100
Drain injury (from drain being pulled by patient or staff when mobilising).100
200
1) Name this drain (a. brand and b. colloquial name).
2) Name 1 defining characteristic.
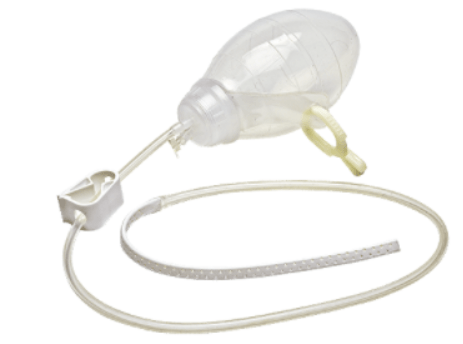
1) Jackson-Pratt 100, Grenade drain 100
Any of the following:
2) Closed100/suction100/active100 drain, facilitates measurement of fluid100.
200
You recognise it's time to change the dressing on one of your patients' Penrose drains.
State 2 actions you would take to maximise patient comfort.
Any two of the following:
PRN analgesia100 15-30 minutes prior to procedure.
Utilise distraction techniques: Buzzy-bee100 , VR Goggles100 , iPad100 , TV100 .
Approach KKIND if appropriate.
300
Name 3 indications/surgeries that may require an open drain.
1) Abscess incision and drainage100
2) Infected surgical wounds100
3) Deep space neck infection100
4) Pilondal cystectomy100
5) Bite wounds100
300
Name 3 indications/surgeries that may require a closed drain.
Any 3 of the following procedures:
(Abdominal/General) Complex appendicectomy100, large bowel resection100.
(Orthopaedic) Joint arthroplasty/replacement100.
(Lymph node clearances100) neck100, axilla100, groin100.
(Breast surgery100) Mastectomy100, augmentation100, reduction100.
(Plastic) Abdominoplasty100, large tissue flaps100, deep wound infection100.
300
Give 3 actions you would take in order to increase patient comfort.
Any 3 of the following:
Regular analgesia and pain management.100
Analgesia prior to procedure (dressing change or removal)100
Drain bag (to ease mobilisation and hide the drain)100
KKIND100
Education for parents and patient (what/why for the drain, how to manage).100
300
1) Name this drain (a. brand and b. colloquial name)
2) How to determine when it is suctioned/de-suctioned.

1) a. Surimex100, b. (Any of the following) Lantern100, Concertina100, Mini-Vac 100.
2) Lengthened when desuctioned, compressed when suctioned 100.
300
1) How often should the dressing be changed on a yates or penrose drain?
2) What kind of dressing should be used?
1) State any 2 of the following: Before it becomes saturated100, usually 50% covered with drainage100, every 3 days100, whenever the dressing becomes wet100 or soiled by the environment100, the dressing is leaking100, or the regime100 determined by the surgical team or Wound CNS.
2) An absorbent dressing100 (fixomull/hypafix100 and combine, mepilex100 etc).
400
How is an open drain secured?
Yates/Penrose drains are secured to the skin100 with a surgically placed100 suture100 to prevent the drain moving100 further in/out of the skin.
400
Name 4 reasons drain output may cease/slow.
Any 4 of the following:
Obstruction in tubing100 /blood clot100 /fat embolism100
Kinked tubing100 /clamped100 /bent100
Not suctioning100 / drain too high from patient body100
Migrated tubing100 /too far out of patient100
Fault in equipment100 /tubing100 /chamber100
Unwanted fluid production has slowed/ ceased 100
400
Name 4 situations where you would escalate care of a drain.
Any of the following:
Cessation of output100
Sudden significant increase in output100
Sudden bright red output100
Purulent / cloudy / unexpected output 100
Resistance on removal 100
Migration of drain from insertion site100
Consistent leaking of drain 100
Suspected infection 100
IF YOU ARE CONCERNED100
400
1) Name this drain
2) What kind of drainage does it facilitate
3) Name two surgeries it can be used for

1) Penrose drain100
2) Passive drainage/open drainage100
3) Any two of the following: Abscess incision and drainage100, deep space neck infection100, pilondial cystectomy100, deep bite wound100, infected surgical wound100.
400
You're completing your hourly checks on your patient with a Jackson-Pratt (grenade) drain. You notice the drain is no longer suctioned.
State 2 reasons why the drain might have de-suctioned and what action would you take?
Any 2 of the following:
The chamber is full100. Requires measurement/ emptying/ resuctioning100.
There may be a fault in the equipment (tubing or chamber)100 . Attempt to aseptically resuction and check equipment for faults100, replace faulty parts100 , alert shift c/o team if not re-suctioning100.
The drain tubing has migrated too far out of the patient and cannot maintain suction 100, to alert shift c/o and team if this has happened 100
500
What is the difference between a yates drain and a penrose drain?
The Penrose drain is a smooth, soft, rounded tube100 used as an open drain. Can sometimes collapse100, limiting drainage.
The Yates drain is a smooth, soft, flat, corrugated100 tube that promotes drainage. Corrugation prevents collapse of the drain100.
If the correct definition is for the correct drain100.
500
Give 2 examples of expected drain output and their meaning.
Any two of the following
1) Bright red blood100 - fresh blood /active bleeding100
2) Haemoserous /diluted blood100 - early stages of healing/ plasma and blood100
3) Serous /clear/straw 100 - later stages of healing100
4) Purulent/ cloudy100 - pus, potential infection100
5) Brown /green100 - potenial bowel contents100
500
State the 5 nursing considerations/observations for drain documentation.
Colour100 , consistency100 , volume100 , patency100 and insertion site100 .
500
1) Name this drain
2) How to determine the level of suction
3+4) How to check if it's actively suctioned/de-suctioned
5) How to check patency

1) Vari-Vac Drain.100
2) By checking the suction indicator/ arrow on the blue dial.100
3+4) The suction indicator /red 'bunny ears' will be crossed when actively suctioned, and will point straight up when not under suction. 100
5) Pull on red tag on the middle of the blue indicator to move fluid along the tubing. 100
500
You're receiving handover for a patient with a Vari-Vac drain (ward/PACU/previous shift).
State 5 things you would check/observe about the drain during handover of the patient.
Any 5 points of the following:
Drain output: is there active bleeding100 in the drain?
Drain patency: is all the tubing unkinked100 /unclamped100 ?
Drain suction: is the drain suctioned100 ? What level suction100 did the team determine and is it documented100 ?
Drain incision site: is there bleeding100 /swelling100 /bruising100 at the insicion site?
Drain dressing: is the dressing intact?
Special orders: is there any special orders for the drain? (remove when output is <30mL/24hrs, send specimen to pathology in the AM, change to high suction in the AM, keep clamped until x time, etc).