A
B
C
D
E
100
In a patient with metabolic alkalosis of unknown origin, what is the most useful lab you can order to help determine the Dx?
Urine Chloride
100
A person who suffers from chronic anorexia is suddenly forced by her mother to eat a meal very high in carbs. Shortly after, the patient collapses. Treatment in the ED shows ECG abnormalities and a depressed respiratory rate. A rapid increase in the serum levels of which compound is most likely responsible for condition?
insulin (or glucose). Insulin causes glucose to rush into cells, along with K, Mg, and PO4
100
Name 3 differentials for hypervolemic hyponatremia if urine sodium levels are less than 20.
CHF, Cirrhosis, nephrotic syndrome
100
A patient presents with a cough x 6 months and a 45lb weight loss. You ask her about this and states that the Jenny Craig plan is just amazing. You aren't convinced and decide to run some labs. PTH is low, serum phos is low, and serum calcium is high. Additionally, CXR shows perihilar nodules consistent with squamous cell carcinoma. What is the most likely cause of the patient's electrolyte imbalance?
paraneoplastic syndrome releases PTHrP
100
This treatment for acute symptomatic hypocalcemia can also be used to reduce the risk of nervous system abnormalities in hyperkalemia
Calcium Gluconate
200
The below image is from a urine microscopy:

The presence of these helps quantify what?
the chronicity of kidney disease, Broad Casts are typically formed in tubules that are dilated from CKD
200
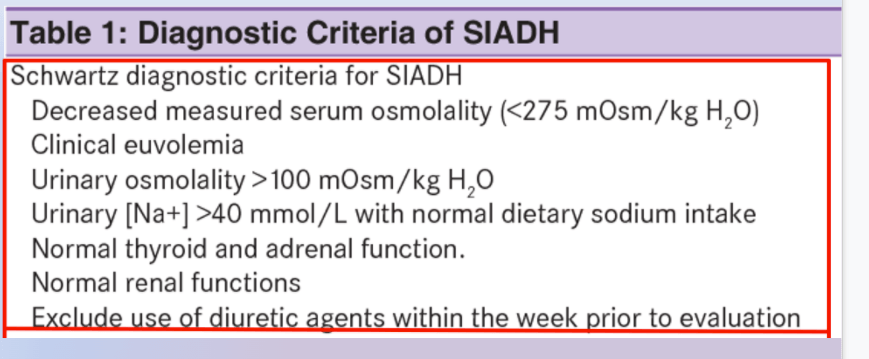
A patient presents with serum osmolality of 260, urine Na of 45, and urine osmolality of 360. What is the most likely Dx?
SIADH
200
A person overdoses on Aspirin, what acid base disorders are they likely to present with?
Respiratory alkalosis and WAGMA
200
A patient presents with complaints of "blood in her urine". Microscopy of a urine sample reveals the following:

The patient states that she has a UTI, as she has had many in the past. Do you agree with her?
No, acanthocytes indicate glomerular damage. Glomerulus is typically spared in pyelonephritis
200
Give the type of RTA that is associated with hyperkalemia
Type IV RTA, also know as hypoaldosteronism
300
A patient presents with fatigue, weight loss and night sweats. Pt has no hx of travel or exposure to anyone that has been outside the US. PE reveals a non-painful, enlarged lymph node in the R cervical chain. If we are thinking this is Hodgkin's lymphoma, what pathognomonic cell must be present in the lymph node biopsy
Reed Sternberg Cells
300
A patient presents with a laundry list of complaints including joint aching, recurrent kidney stones, persistent stomach ulcers and abdominal pain. Labs indicate that values of PTH are high. Assuming the issue is caused by an electrolyte imbalance, what is the first thing you should do to treat?
Hydration, Hydration, Hydration.
300
A 70 Yo male presents with red, painful extremities and severe itching after a hot shower. Microscopy reveals this:

A mutation in what gene could be responsible for the patients condition?
JAK2
300
A 14 Yo female presents with fever and petechiae. PTT and PT are normal, Ristocetin assay is normal, thrombocyte levels are at 50,000. Peripheral blood smear shows this:

The patient most likely became sick due to a secreted toxin from what bacteria (give the specific strain)
E. Coli O157:H7
300
A patient submits a sample for urinalysis and reveals the following:

If we suspect that the patient has a certain condition causing this, what other urine compound in urine could we test for that could provide a dx?
check urine protein. Oval fat bodies typically appear in nephrotic syndrome
400
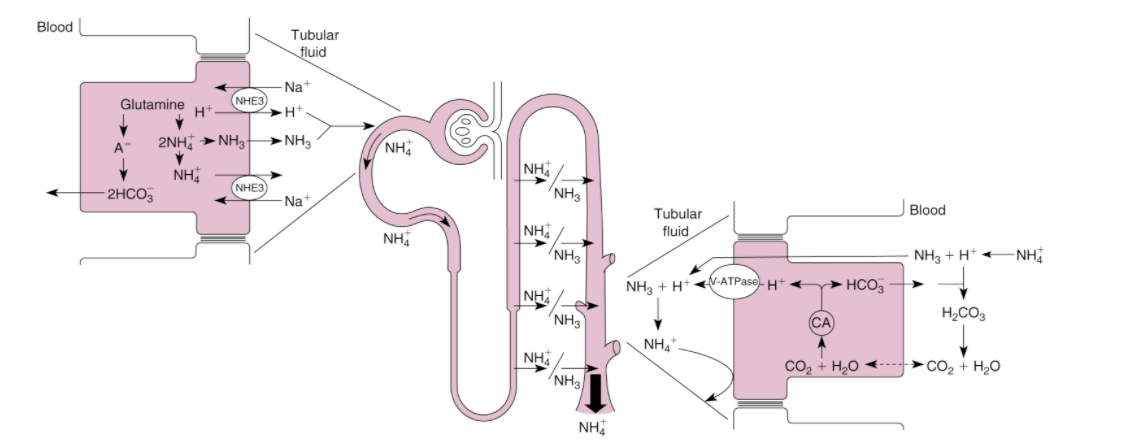
A patient with RTA type I presents with signs and symptoms of azotemia (high blood urea nitrogen). Urinalysis reveals that the urine anion gap is positive. Despite this, samples take from the PCT show that NH4 is present in urine at that location. What is the mechanism by which NH4 is not being secreted?
NH4 is being produced in the proximal tubule and is reabsorbed the TAL. It then splits into NH3 and H+. NH3 can freely diffuse into the collecting duct, but H+ must be secreted. If H+ is not present in the tubular fluid to re-create NH4, then NH3 will simply diffuse back into the interstitial fluid, and subsequently re-enter systemic circulation, eventually becoming urea and consuming the HCO3 that was generated when it was made in the PCT. In RTA Type I, H+ secretion in the CT is impaired, thus so is NH4 excretion.
400
A patient presents with a bleeding disorder and a prolonged PTT. You conduct a mixing study to determine the cause. After mixing the pt's plasma with plasma from a donor, PTT drops back within the normal range. Generally speaking, what is the cause?
Some factor deficiency
400
A patient presents to you with signs of metastatic calcification (carotid bruits, sub-epidermal CaPO4 deposits, etc). Labs reveal a markedly elevated level of phosphate. The patient says they don't need you to prescribe anything, because their homeopath gave them a pill he designed, which will increase excretion of phosphate in the urine. How is the Homeopath scamming the patient?
There are no medication that increase phosphate excretion.
400
A patient with a granulomatous disease presents with muscle weakness and reduced DTRs. CMP shows reduced serum calcium levels. What enzyme present within the macrophages of the granulomas could cause the patient's condition?
alpha 1 hydroxylase: increased vit D activation and calcium and phos absorption
400
A patient presents to the ED with numbness and tingling in his hands and feet. PE reveals loss of positional sense and vibratory sensation of the big toes. Peripheral blood smear shows RBCs with a diameter of 15um and hypersegmented neutrophils. SHx is positive for gastric bypass x 5 years ago. What form of folate is most likely to be accumulated inside the body?
N5-THF

500
The final step of secondary hemostatis is the conversion of a "soft-clot" to a "hard-clot" via the action of a transglutaminase. What compound of the coagulation cascade serves to activate this Factor?
Thrombin, converts FXIII to FXIIIa
500
A patient presents with stupor, decreased mental status, nausea and vomiting. ABG and CMP reveals pH: 7.05, Anion gap of 18, decreased pCO2 and bicarb, and an osmolar gap 20 units higher than calculated. UA microscopy shows this:

Treatment is initiated, and the patient improves somewhat. They state they haven't been eating anything out of the ordinary, and haven't ingested any substances. Why should you call the police?
Calcium oxylate dihydrate crystals are commonly seen in Antifreeze poisoning (ethylene glycol). This poor dude's wife might be trying to get her life insurance check sooner than later.
500
When platelets bind to vWF via GP Ib, they degranulate and release ADP, which acts in an autocrine manner by binding P2Y12 receptors. This causes a conformational change in Gp IIb-IIIa receptors, allowing them to bind what molecule?
fibrinogen
500
A patient appears with complaints of persistent nosebleeds. He states that they take forever to stop. Analysis reveals a genetic defect in GP IIb-IIIa. What would we expect platelet levels on a CBC to look like?
They would be normal
500
A patient with recurrent DVTs presents to an ED for evaluation of a swollen left calf. After extensive evaluation, it is determined that the cause of the coagulopathy is due to a protein C deficiency. The intern working the case prescribed warfarin and calls it a day. Why should he lose he just quit his job and go flip burgers?
You can't use warfarin initially with PC or PS deficiency, as it can cause a hypercoagulable state and lead to skin necrosis