Not too bad
Kinda bad
VA ED
Whacky Vision
Good Luck
100
Retrochiasmal lesions create a (homonymous or non-homonymous) visual defect that respects the (vertical or horizontal) midline.
homonymous, vertical
100
Where is the lesion?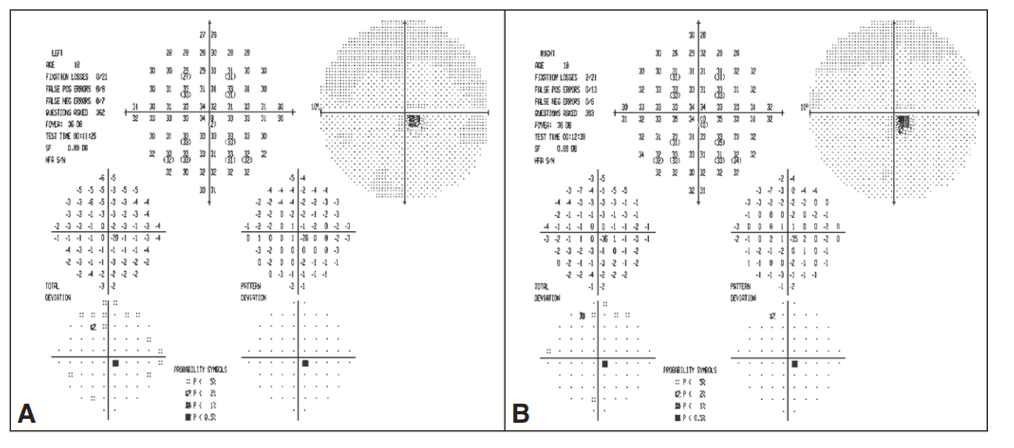
Left occipital lobe, just the tip.
100
Kishor gets a call at 4:29pm from the VA ED while playing Clash Royale: "Hey uh I got a 67 year old guy down here says all of a sudden he couldn't see anything out of his right eye while driving a semi truck but it got better after 20 minutes. He never stopped driving. Our tonopen isn't working, do you think he has glaucoma?" Kishor looks at his chart and sees that no other work up has been done.
What should Kishor do:
A. Deeply sigh, and continue his Clash match.
B. Deeply sigh, and advise a vascular work up - what should this include?
A. You still get full credit.
B. CT Head, CTA Head and Neck, can also get MRI Head / MRA, carotid US
100
On the way back from Harlan with Dr. Pearson, Elizabeth gets pulled over for speeding. After getting the ticket, she gets a migraine and then starts seeing afterimages of the cars that are passing her while she goes 45 mph on the interstate. What is this called, and what can cause this?
Palinopsia specifically illusory palinopsia
Migraines, hallucinogenic drugs LSD, and other medications: clomiphene, nefazodone, topiramate, trazodone, zonisamide
100
What is the uhthoff phenomenon?
Worsening of prior neurological symptoms with exertion or temperature
200
Lesions of the optic radiations classically produce (incongruous or congruous) homonymous VF defects, whereas lesions more posteriorly produce a more (incongruous or congruous) defect.
incongruous, congruous
Bonus what is the most common cause of homonymous hemianopias?
200
Where is the lesion?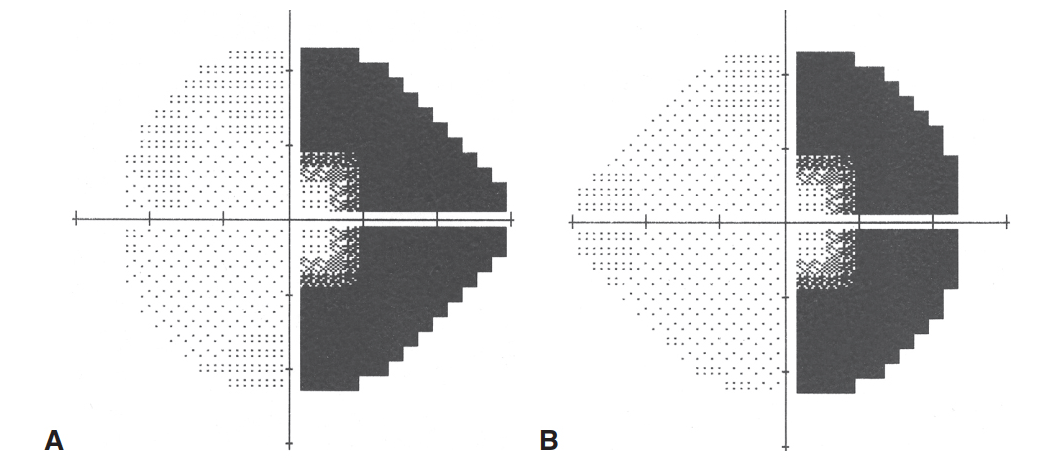
Left occipital sparing the tip.
200
Z gets a call from the VA ED at 4:20 pm while he is re-applying his late afternoon Giorgio Armani cologne but accidentally sprays it his eyes. Maddie Edwards then picks up the phone and the ED provider says he has a sweet 67 yo lady with a nagging left sided headache and starting to get blurred vision in her left eye. What other symptoms could the patient have that Maddie should ask the ED provider? And what labs?
GCA symptoms: scalp tenderness, jaw claudication, weight loss, proximal muscle weakness, malaise, fever
ESR, CRP, CBC
200
What is Anton Syndrome? What is Charles (Ryan's actual first name) Bonnet Syndrome
1. Cortical blindness but denies being blind.
2. Cortical blindness, knows they are blind, but have visual hallucinations.
200
What is Pulfich phenomenon?
A visual illusion where a flat, side-to-side moving object is falsely perceived as moving in a three-dimensional, curved or elliptical path.
300
Name the 4 parts of the retrochiasmal visual pathway in order.
Optic tract
LGN - lateral geniculate nucleus
Optic radiations - temoral, parietal, occipital lobes
Visual cortex
300
Where is the lesion based on this VF?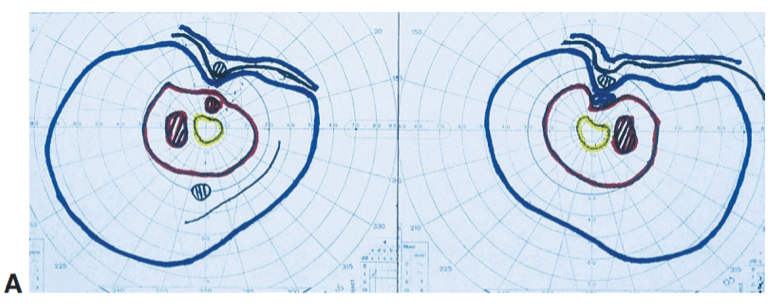
Left temporal lobe / Meyer Loop
300
DAILY DOUBLE: What toppings do I get on my steak at Texas Roadhouse?
None, let the meat speak.
300
A patient says that he is able to write but is having trouble reading what he just wrote. Assuming his handwriting is better than David's, damage to what area of the brain can cause this? And what is the Neuro nerd way of describing this?
Splenium of corpus callosum
Alexia without agraphia
300
What is Balint Syndrome?
Damage to the posterior parietal and occipital lobes of the brain resulting in the following:
- Simultanagnosia: inability to perceive / focus on more than one object at a time.
- Optic ataxia: poor hand eye coordination
- Oculomotor apraxia: inability to voluntarily shift gaze to a new target
400
What is bow tie optic atrophy, and why does it happen anatomically?
Bow tie optic atrophy occurs in lesions to the optic tract. There is vertical/polar atrophy in the ipsilateral eye, and horizontal atrophy in contralateral eye.
The temporal fibers arc over and enter the superior/inferier ONH creating vertical bow tie atrophy.
The nasal fibers and the PM bundle from the contralateral eye enter the ONH horizontally
400
Where is the lesion and which artery was affected?
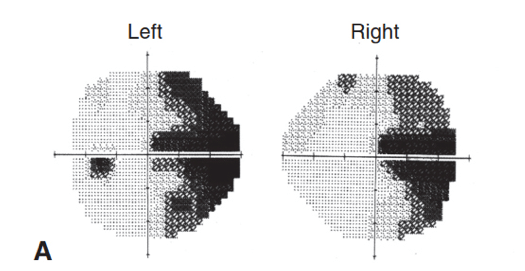
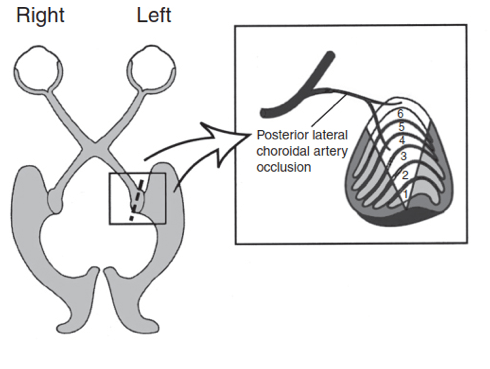
400
Cody Hayden gets a call from the VA ED while evaluating his third VKH patient of the night. "Hey uh I got this 32 year old lady here she says she all of a sudden she see anything out of her right eye. Can you see her?" Cody asks if there is any other history, and he replies with "she's allergic to mayonnaise." Cody hangs up and sighs, but then sees she had a history of 3 miscarriages. What labs should Cody think about ordering. Name at least 5.
Hypercoag work up
- Lupus anticoagulant, antiphospholipis, anticardiolipin, PT/PTT, CBC, protein C, protein S, antithrombin, factor V leiden, and some others that I can't remember
400
Leigh finally invents a Time Machine using a 4th Dimensional Leigh Light (Trademarked) and transports herself to 65 millions years in the past. She is immediately confronted by a T Rex. She then remembers that in Jurassic Park that it can only see movement, so she stood still, but was immediately eaten. What is this phenomenon called?
Riddoch phenomenon / statokinetic dissociation
400
What is Gerstmann Syndrome? And where is the lesion?
Combination of acalculia, agraphia, finger agnosia, left right confusion.
Dominant parietal lobe
500
Why is there a mild APD in optic tract syndrome. And which eye does the APD occur - ipsi or contralateral to the lesion?
There is greater sensitivity in the nasal retina, and there is more crossed than uncrossed papillary fibers in the optic tract in the contralateral eye.
500
Where is the lesion and which artery was affected?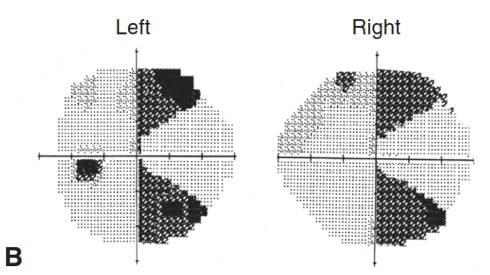
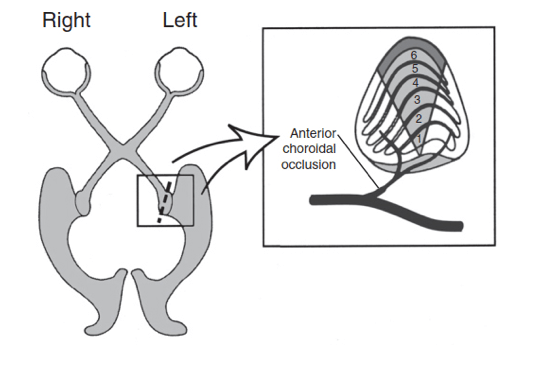
500
Maddie Mitcham gets a call from the VA ED on Thursday night while baking the department her chocolate chip oatmeal cookies. The ED says "Hey uh I got this guy he had a CEA for long standing R ICA 95% stenosis about a week ago. He's coming in with right eye pain and his pressure is like 45." He has no history of POAG, is pseudophakic, and no other glaucoma related risk factors, in fact his IOP was trending on the lower side in prior visits with LOD. What could have been the cause of his sudden increase in IOP? What should Maddie look for on exam? And what should she do?
Ocular re-perfusion syndrome in a patient with likely history of OIS.
Signs of OIS: mid peripheral hemorrhages, flare without cell, dilated von-tourtous veins, NVI/D/E
IOP drops for now, if NV is present then antiVEGF and PRP later in clinic
500
Kishor comes up to you and says that as he was about to fall asleep last night, he had a vision that his Fantasy Football team will win this year. You know that this is not possible. What type of hallucination is this? And what if he had this vision when he woke up this morning instead?
Hypnagogic - falling asleep
Hypnopompic - waking up
500
Which area of the brain, if damaged, can cause abnormalities in optokinetic nystagmus? And how can you elicit the abnormal response?
Damage to the pursuit pathways in the posterior parietal lobe. Limited OKN response when the moving targets go to the side of the lesion.